Просмотр новости
Найдите то, что Вас интересует
 Спутники
 РН
 SpaceX
 Роскосмос
 NASA
СпутникиРНSpaceXРоскосмосNASASolid pseudopapillary tumors (SPT) of the pancreas are rare neoplasms, representing less than 2% of all pancreatic tumors, and predominantly affecting young women. Their clinical and radiological presentation is often heterogeneous, which may delay or complicate the diagnosis. Complete surgical resection is associated with excellent prognosis; however, long-term follow-up remains necessary due to the risk of late recurrence. We report the case of a young woman who presented with a pancreatic mass revealed by vague non-specific abdominal pain. The diagnosis was confirmed by histopathological and immunohistochemical examination of the resected surgical specimen. This case highlights the diagnostic challenges associated with SPT and emphasizes the importance of considering this entity in the differential diagnosis of pancreatic tumors in young patients, even in the absence of specific biological abnormalities.
A solid pseudopapillary tumor (SPT) of the pancreas is a rare pancreatic neoplasm, accounting for approximately 2% of exocrine pancreatic tumors.1,2 It is generally characterized by a low malignant potential and a striking predilection for young women. Although its incidence appears to be increasingly recognized with the widespread use of cross-sectional imaging, the pathogenesis of SPT remains incompletely elucidated. Several hypotheses, including hormonal and embryological mechanisms, have been proposed, supported by its marked female predominance and the frequent expression of progesterone receptors by tumor cells. Clinically, SPT often follows an indolent course and may remain asymptomatic for a prolonged period. When symptoms occur, they are usually nonspecific, such as abdominal discomfort, pain, or a palpable mass. Consequently, a substantial proportion of SPTs are discovered incidentally during abdominal imaging performed for unrelated clinical indications.
Because of this nonspecific presentation, diagnosis relies primarily on histopathological examination. Surgical resection remains the treatment of choice and is usually associated with an excellent prognosis, even in cases with large tumors or limited local invasion.3
This case report provides additional insight into the management of solid pseudopapillary tumors in routine clinical practice. It reflects the challenges encountered in a resource-limited setting, particularly in the absence of endoscopic ultrasound-guided fine needle aspiration (EUS-FNA), which led to direct surgical management. The case is also notable for a 48-month follow-up showing no evidence of recurrence; however, this duration remains insufficient to exclude the possibility of late relapse. In addition, it adds to the relatively limited data available on SPT in African patients, who remain underrepresented in the in published series.
A 19-year-old woman of African origin, a high school student with no history of abdominal trauma, surgery or smoking was admitted for evaluation of chronic abdominal pain located in the epigastrium and the left hypochondrium. She also had no relevant family medical history. The pain had started six months before admission and had progressively worsened. It was associated with an deterioration of her general condition, and she reported an 11 kg weight loss during this period.
The physical examination was unremarkable,except for mild epigastric tenderness. Laboratory tests, including serum CA 19-9 and carcinoembryonic antigen (CEA), were within normal limits. Abdominal Doppler ultrasonography showed a round, well-defined vascular mass. It measured approximately 42 mm and extended from the retroperitoneum to the lower pole of the ipsilateral kidney. It was heterogeneous, predominantly cystic, with hyperechoic components.
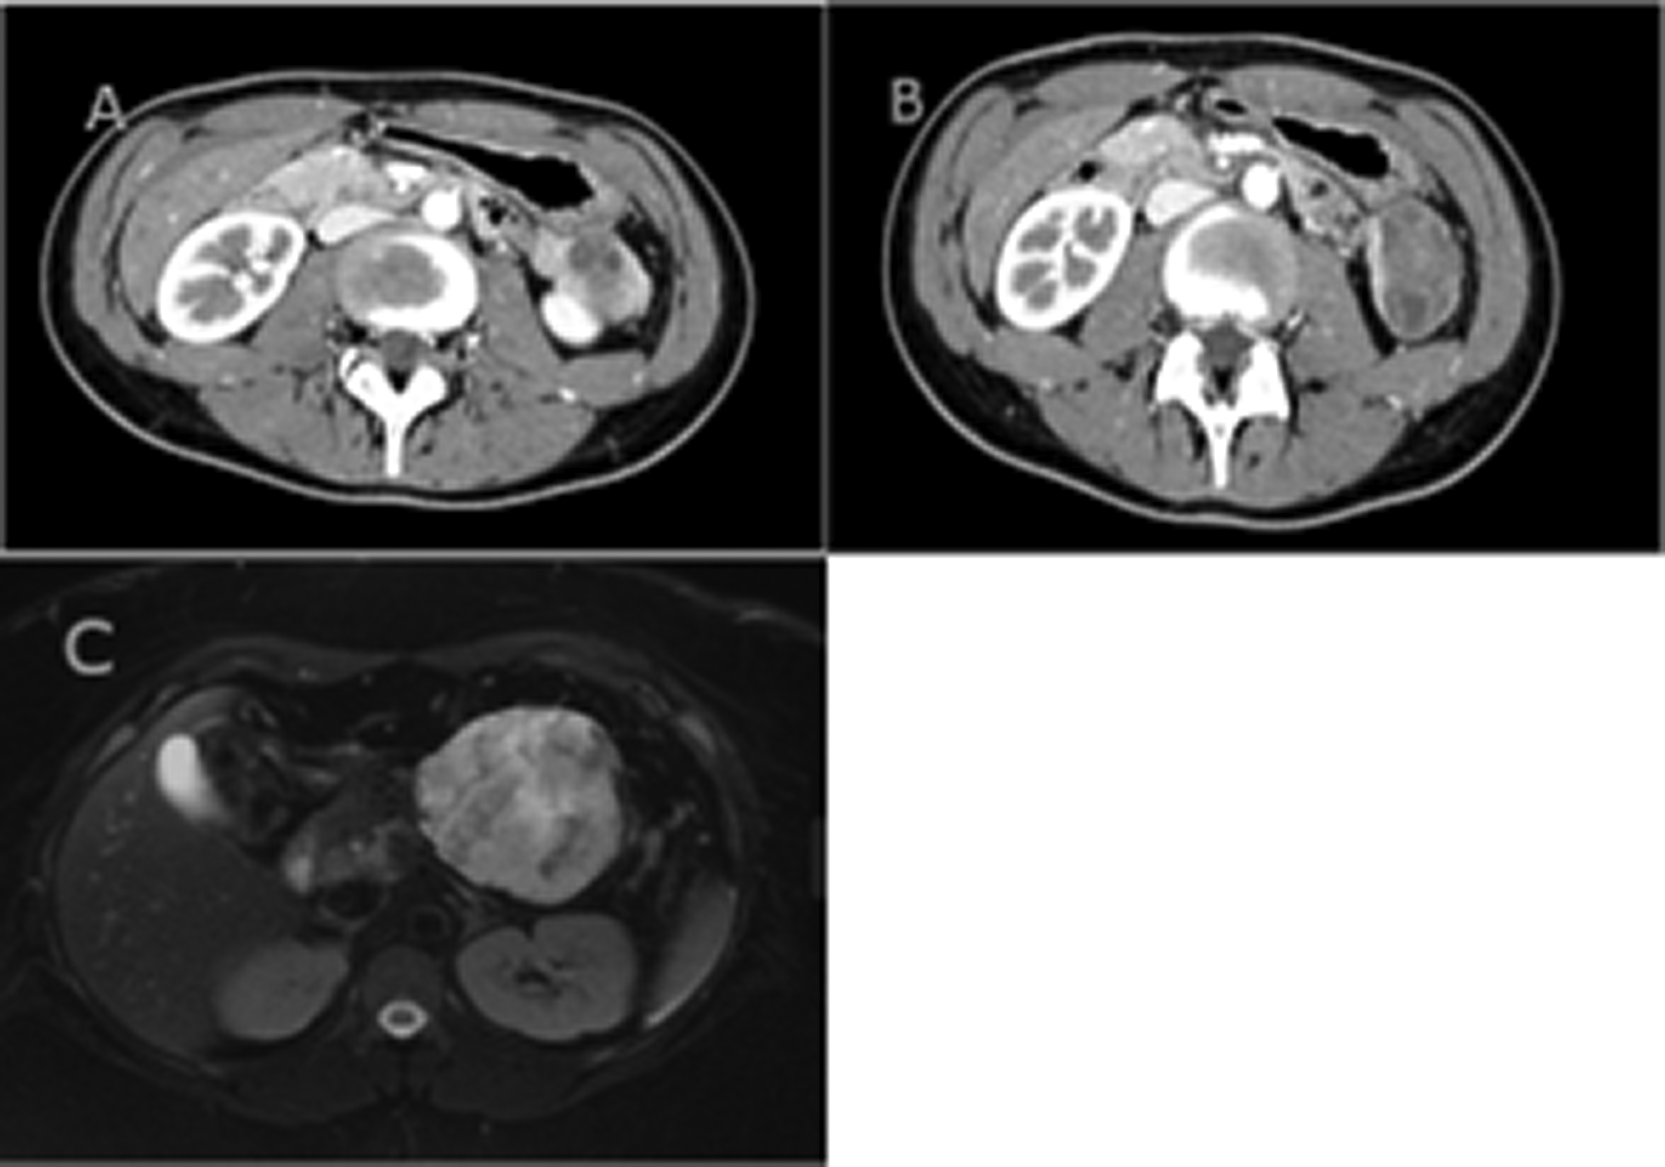
Computed tomography (CT) and magnetic resonance imaging (MRI) revealed a 44 × 42 × 34 mm solid masslocated in the pancreatic tail. The lesion was isodense on non-contrast imaging, with moderate and heterogeneous enhancement after contrast administration, and contained scattered cystic areas. The mass had well-defined margins and extended inferiorly toward the descending colon without signs of compression or invasion. The peritoneal fat was normal in appearance (Figure 1). Hepatic and pancreatic laboratory tests were normal. Endoscopic ultrasound-guided biopsy was not available in our hospital service; therefore, surgery was performed without a preoperative histological confirmation.
Intraoperatively a 5-cm exophytic tumor arising from the inferior border of the pancreatic tail was identified. There was no locoregional invasion or distant metastasis. The tumor was completely resected by a distal pancreatectomy, and the postoperative course was uneventful. Histopathological examination revealed a well-circumscribed tumor with mixed solid and cystic components. Microscopically, the lesion was composed of uniform, poorly cohesive polygonal cells arranged in solid sheets and pseudopapillary structures surrounding delicate fibrovascular cores. The tumor cells exhibited eosinophilic cytoplasm and round to oval nuclei without significant atypia. No significant mitotic activity was observed. Immunohistochemical staining demonstrated CD10 positivity in tumor cells, supporting the diagnosis of solid pseudopapillary tumor of the pancreas (Figure 2). The patient had a favorable postoperative course, with normal ultrasonographic follow-up at 3, 12, 24, and 48 months and CT scans at 12, 24, and 48 months, showing no evidence of recurrence or residual disease.
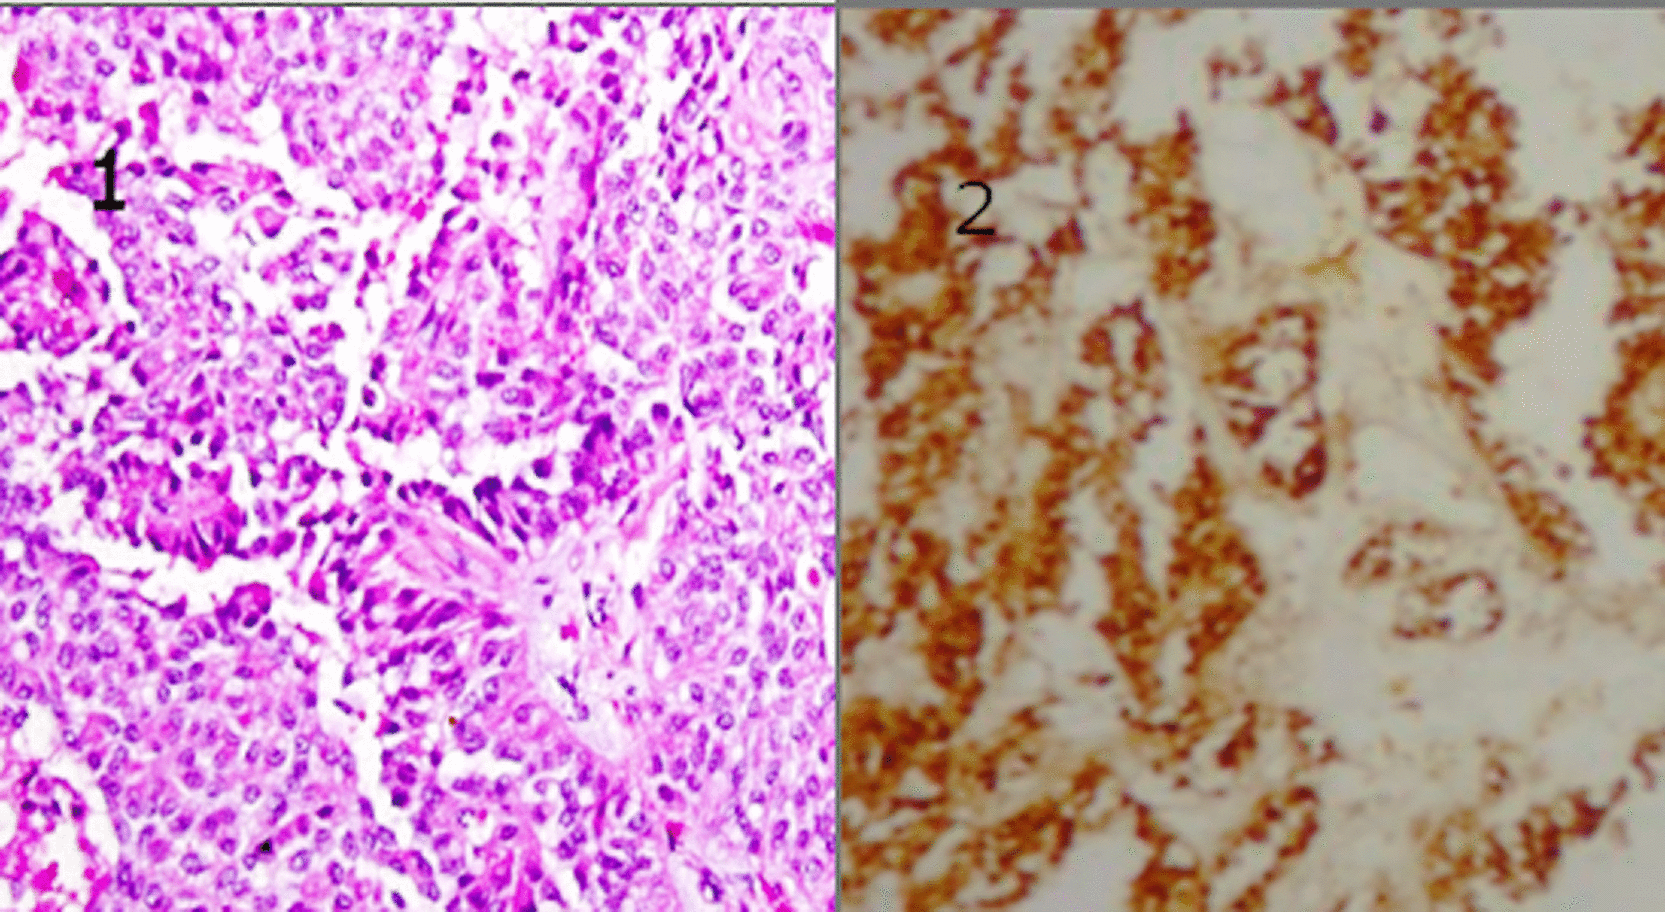
(1) Hematoxylin and eosin staining showing characteristic pseudopapillary architecture with fibrovascular cores and uniform tumor cells (original magnification ×200). (2) Immunohistochemical staining demonstrating diffuse CD10 positivity in tumor cells.
Solid pseudo-papillary tumor (SPT) of the pancreas is a rare pathological entity first described by Frantz in 1959. It accounts for approximately 0.7 to 2.7% of all exocrine pancreatic tumors and less than 5% of cystic pancreatic neoplasms.4 The rarity of this entity makeseach reported case valuable, particularly in improving diagnostic awareness and refining management strategies.
SPT predominantly affects young women, with more than 90–95% of cases occurring in females and a mean age at diagnosis of approximately 22 years.5,6 This epidemiological profile was consistent with our patient. Although rare cases in males and elderly patients have also been reported.7 The etiopathogenesis of SPT remains unclear. Two main hypotheses have been proposed: a hormonal origin suggested by the female predominance and progesterone receptor expression, and an embryological origin involving totipotent pancreatic stem cells capable of multidirectional differentiation.8
In most cases, SPT presents with non-specific symptoms. Abdominal pain is the most frequent mode of revelation, reported in nearly 50–60% of patients, while incidental discovery on imaging performed for unrelated reasons is increasingly common. In our patient, chronic non-specific abdominal pain was the only presenting symptom, and no specific biological abnormalities were observed. This reinforces the limited diagnostic value of laboratory investigations and highlights the central role of imaging in the diagnostic pathway.
SPT can arise in any part of the pancreas but shows a predilection for the body and tail, accounting for approximately 60–65% of cases. Rare extra-pancreatic localizations, including retroperitoneal, mesocolic, or hepatic sites, have been described and support the hypothesis of origin from ectopic pancreatic tissue or pluripotent stem cells. Macroscopically, SPT is usually a large, well-circumscribed mass, often exceeding 10 cm in diameter, with a fibrous capsule and mixed solid-cystic appearance.9,10
Radiologically, abdominal ultrasound typically reveals a well-defined heterogeneous mass. On computed tomography, SPT appears as a hypodense lesion with limited enhancement and mixed solid and cystic components. Magnetic resonance imaging often shows heterogeneous hyperintensity on both T1- and T2-weighted sequences, with a hypointense peripheral capsule. Although imaging findings are highly suggestive, they are not pathognomonic, as several cystic pancreatic lesions may mimic SPT. In resource-limited settings, the lack of endoscopic ultrasound-guided fine needle aspiration (EUS-FNA) may lead to upfront surgery, as in our case. Nevertheless, EUS-FNA currently represents a reliable diagnostic tool, with reported accuracy exceeding 80% for pancreatic tumors.6,11
Histological examination remains the gold standard for diagnosis. Typical microscopic features include uniform polygonal cells arranged in solid sheets and pseudopapillary structures surrounding a fibrovascular core. Immunohistochemistry plays a crucial role, with tumor cells classically expressing CD10, vimentin, alpha-1 antitrypsin, and β-catenin. Nuclear accumulation of β-catenin, reflecting activation of the Wnt signaling pathway, is currently considered one of the most specific hallmarks of SPT.11
From a therapeutic perspective, surgery remains the cornerstone of treatment. Complete resection is associated with excellent outcomes, even in cases with local invasion or limited metastatic disease. Our patient underwent distal pancreatectomy with favorable postoperative evolution. Parenchyma-preserving procedures, such as enucleation or central pancreatectomy, are increasingly favored when feasible, as they reduce the risk of long-term endocrine and exocrine insufficiency while maintaining excellent oncological outcomes. Minimally invasive approaches, including laparoscopic and robotic surgery, have also demonstrated safety and efficacy.
Although SPT is generally considered a tumor with indolent behavior, it should not be regarded as strictly benign. Malignant features, including vascular invasion, perineural invasion, and distant metastases, are reported in approximately 10–15% of cases. The liver remains the most common metastatic site. Importantly, late recurrences have been described up to 10–15 years after initial surgery, emphasizing the need for long-term follow-up even in non-metastatic cases.12 In our case, although no recurrence was observed at 48 months, this follow-up duration remains limited and does not allow definitive conclusions regarding cure.
In contrast to pancreatic ductal adenocarcinoma, which is associated with a dismal prognosis and a 5-year survival rate generally below 10%, solid pseudopapillary tumors exhibit an indolent clinical course and an excellent prognosis, with reported 5-year survival rates exceeding 95% following complete surgical resection. This striking difference highlights the importance of accurate diagnosis and appropriate surgical management.
This case highlights three important clinical messages: (1) SPT should be considered in young women presenting with pancreatic masses; (2) the absence of EUS-FNA should not delay curative surgery when imaging is suggestive; and (3) long-term surveillance is mandatory despite excellent short-term prognosis. Further multicenter studies are required to define optimal follow-up strategies and to clarify the molecular determinants of malignant transformation in SPT.
Solid pseudopapillary neoplasm of the pancreas is a rare tumor with low malignant potential and excellent prognosis after complete surgical resection, although long-term surveillance is essential given the potential for late recurrence. Diagnosis relies on histopathology and immunohistochemistry, as clinical and biological features are often non-specific. This case underlines the importance of considering SPT in young women presenting with pancreatic masses and supports early surgical management when imaging findings are suggestive. Long-term follow-up remains essential due to the risk of late recurrence.
Written informed consent was obtained from the patient for publication of this case report and any accompanying images.
According to our institutional guidelines, ethical approval is not required for single case reports. All procedures performed in this study were in accordance with the ethical standards of the institutional and national research committee and with the Declaration of Helsinki.